Plantar Fasciitis and Heel Pain: Causes, Related Conditions and Treatment
Heel pain is one of the most common reasons people see a podiatrist, and plantar fasciitis is the most common cause. Around 1 in 10 people will develop plantar fasciitis at some point in their life. But not all heel pain is plantar fasciitis. Heel spurs, bursitis, Achilles problems, a thinning heel fat pad, an irritated nerve or a stress fracture can all cause pain in the same small area.
This guide explains how each condition differs, what puts you at risk, how heel pain is diagnosed and the full range of treatments — from simple stretches at home to injections, shockwave therapy and surgery. You’ll also find a daily exercise routine you can start today.
What is plantar fasciitis?
Plantar fasciitis is irritation and small-scale damage of the plantar fascia, the thick band of tissue that runs from your heel bone to the base of your toes. The plantar fascia works like a bowstring: it holds up your arch and absorbs shock every time your foot hits the ground.
When the load on this band is more than it can recover from, tiny tears form where it attaches to the heel bone. Doctors now often call it plantar fasciopathy or plantar heel pain, because long-standing cases show tissue degeneration rather than ongoing inflammation. That matters for treatment: it explains why rest alone rarely fixes it and why gradual strengthening helps.
Classic symptoms
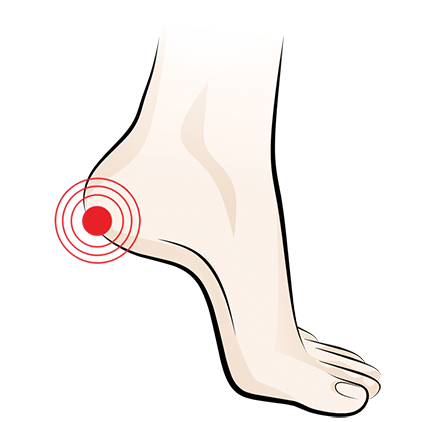
- Sharp or stabbing pain under the heel, usually towards the inside
- Pain with the first steps in the morning, or after sitting for a while (“first-step pain”)
- Pain that eases as you warm up, then returns after long periods of standing or walking
- Tenderness when you press the bottom of the heel
- Sometimes an ache or tightness along the arch
Why it hurts most in the morning
While you sleep, your foot rests with the toes pointing down and the plantar fascia shortens. Your first steps stretch it suddenly, pulling on the damaged attachment at the heel. The pain usually settles after a few minutes as the tissue warms up and lengthens.
How long does it last?
Most people improve within 6–12 months with simple, consistent self-care, and around 80–90% recover without surgery. Earlier treatment usually means faster recovery. Read more in How long does plantar fasciitis take to heal?
Other causes of heel pain
Plantar fasciitis accounts for most heel pain, but several other conditions cause pain in or around the heel. Some often occur alongside plantar fasciitis; others need quite different treatment.
Heel spurs (calcaneal spurs)
A heel spur is a small bony growth on the underside of the heel bone, where the plantar fascia and the small foot muscles attach. Spurs form slowly in response to years of pulling and pressure at that spot. They are very common in people with plantar fasciitis, but also show up on X-rays of people with no pain at all.
In most cases the spur itself is not what hurts — the pain comes from the irritated soft tissue around it. That’s why heel spurs are treated the same way as plantar fasciitis, and surgery to remove a spur is rarely needed. See orthotic insoles for heel spurs.
Heel bursitis
A bursa is a small fluid-filled sac that reduces friction between tissues. When it becomes inflamed, it causes swelling and a deep, aching pain. Two types affect the heel:
- Retrocalcaneal bursitis — the bursa between the Achilles tendon and the back of the heel bone. Pain is at the back of the heel, just above where the tendon attaches, and is worse when you rise onto your toes, walk uphill or start activity.
- Inferior calcaneal (sub-calcaneal) bursitis — a bursa under the heel. It feels similar to plantar fasciitis but is often more of a constant, bruise-like ache with some puffiness under the heel.
A related problem, Haglund’s deformity (“pump bump”), is a bony enlargement at the back of the heel that rubs on stiff shoe backs and often triggers retrocalcaneal bursitis.
Insertional Achilles tendinopathy
This is degeneration of the Achilles tendon right where it attaches to the back of the heel. It causes pain and stiffness at the back of the heel, often worst in the morning and after exercise, and sometimes a bony bump. It frequently occurs together with retrocalcaneal bursitis and Haglund’s deformity. Read more about Achilles tendonitis.
Fat pad atrophy and heel pad syndrome
Your heel sits on a thick cushion of fat that absorbs impact. With age, long-term steroid injections, or years of high impact, this pad can thin out or lose its springiness. The result is a deep, bruised pain in the centre of the heel, worse on hard floors and when barefoot, and usually without the first-step morning pattern of plantar fasciitis. Cushioned heel cups and soft-soled shoes help most.
Baxter’s nerve entrapment
A small nerve (the first branch of the lateral plantar nerve, also called Baxter’s nerve) can be pinched near the inside of the heel. It causes burning, shooting or electric pain on the inner heel that can spread across the sole, and it often doesn’t settle as you warm up. It is estimated to cause a meaningful share of heel pain that doesn’t respond to standard plantar fasciitis treatment.
Tarsal tunnel syndrome
The tibial nerve runs through a narrow channel on the inside of the ankle. When it’s compressed, you may feel burning, tingling, pins and needles or numbness on the inner ankle, heel and sole, often worse at night or after long periods on your feet.
Calcaneal stress fracture
A stress fracture is a tiny crack in the heel bone from repeated impact. It’s most common in runners, military recruits and people who’ve suddenly increased their walking or training. The pain is felt across the whole heel, gets steadily worse with weight-bearing, and squeezing the sides of the heel hurts. It needs a medical diagnosis and a period of offloading.
Sever’s disease (children)
Sever’s disease (calcaneal apophysitis) is the most common cause of heel pain in active children aged about 8–14. The growth plate at the back of the heel becomes irritated by the pull of the Achilles tendon during growth spurts. It settles once the growth plate closes. See children’s heel pain (Sever’s disease).
Less common causes
Heel pain can also come from inflammatory arthritis (such as ankylosing spondylitis, psoriatic or reactive arthritis), a plantar fascia rupture after a sudden injury, nerve irritation from the lower back (sciatica), bone bruises, and, rarely, infection or tumours. These are why persistent or unusual heel pain should be checked by a health professional.
How to tell heel conditions apart
Where the pain is, and when it’s worst, are the best early clues. Use this as a guide only — several conditions can occur together.
| Condition | Where it hurts | Typical pattern | Key clue |
|---|---|---|---|
| Plantar fasciitis | Under the heel, towards the inside | Worst on first steps in the morning or after rest; eases, then returns | Sharp “first-step” pain |
| Heel spur | Under the heel | Same as plantar fasciitis (spur itself usually painless) | Seen on X-ray |
| Fat pad atrophy | Centre of the heel pad | Deep bruise-like ache, worse on hard floors and barefoot | No first-step pattern; thin, soft heel pad |
| Inferior calcaneal bursitis | Under the heel | Constant ache, some swelling | Puffy, tender heel pad |
| Retrocalcaneal bursitis | Back of the heel, above the tendon insertion | Worse rising on toes, uphill, in stiff shoe backs | Swelling either side of the Achilles |
| Insertional Achilles tendinopathy | Back of the heel, at the tendon insertion | Morning stiffness, pain after exercise | Tender bony bump at the back of the heel |
| Baxter’s nerve / tarsal tunnel | Inner heel, may spread to sole | Burning, tingling, numbness; can be worse at night | Nerve-type symptoms |
| Calcaneal stress fracture | Whole heel | Steadily worse with weight-bearing | Squeezing the sides of the heel hurts |
| Sever’s disease | Back and sides of the heel | During and after sport | Child aged about 8–14 |
When to see a doctor straight away
- Severe pain and swelling near the heel after an injury, or you can’t put weight on the foot
- Heel pain with fever, redness or warmth (possible infection)
- Numbness or tingling that is spreading, or weakness in the foot
- Heel pain with swollen joints, back pain or eye inflammation (possible inflammatory arthritis)
- Pain in both heels that started without any change in activity
- You have diabetes and notice any heel pain, skin change or wound
Book a routine appointment with a GP, podiatrist or physical therapist if your heel pain hasn’t improved after 6–8 weeks of self-care.
Risk factors for heel pain
Heel pain usually builds up when the load on your heel outpaces your body’s ability to recover. The most common contributors are:
- Age — most common between 40 and 60
- Body weight — a higher BMI is one of the strongest risk factors for plantar fasciitis
- Long hours on your feet, especially on hard floors (nurses, teachers, retail, warehouse and factory workers)
- A sudden increase in activity — new running program, more walking, a holiday on foot, a new sport such as pickleball
- Tight calf muscles or Achilles tendon, and limited ankle flexibility
- Foot shape — flat feet and over-pronation, or high, rigid arches
- Unsupportive footwear — worn-out shoes, thin flat soles, walking barefoot on hard floors
- Running and jumping sports
How heel pain is diagnosed
Most heel pain is diagnosed from your history and a physical examination. A clinician will ask when the pain started, when it’s worst, and what you do on your feet, then press on specific points of the heel and check your calf flexibility, foot posture and walking.
Imaging is only needed when the diagnosis is unclear or the pain isn’t improving:
- X-ray — shows heel spurs, Haglund’s deformity, arthritis and some fractures
- Ultrasound — measures plantar fascia thickness (over about 4 mm suggests plantar fasciitis) and shows bursitis and Achilles changes
- MRI — detects stress fractures, fat pad changes and other soft tissue problems
- Nerve conduction studies — when nerve entrapment is suspected
- Blood tests — when inflammatory arthritis is suspected

Treatment options for plantar fasciitis and heel pain
Footlogics orthotics are very effective and in most cases a difference is felt within a few days or wearing the insoles. However, there are alternative treatment methods you should pursue in addition to wearing orthotics. The five most common treatments are:
Most heel pain gets better with simple, consistent self-care, and around 90% of people with plantar fasciitis never need surgery. Treatment usually works step by step: start with the basics, then add clinician-led and advanced treatments only if pain hasn’t settled after 3–6 months. Combining several treatments works better than relying on any single one. For the plantar-fasciitis-specific detail, read Plantar Fasciitis Treatment Options: The Complete Guide.
Step 1: Self-care you can start today
- Load management (relative rest) — cut back, don’t stop. Reduce the activities that aggravate the pain (running, jumping, long periods standing) and swap in low-impact exercise such as cycling, swimming or rowing. Build back up gradually as pain settles.
- Stretching and strengthening — the most important long-term treatment. Calf and plantar fascia stretches reduce first-step pain; progressive heel-raise strengthening helps the tissue rebuild. See the exercise routine below.
- Supportive footwear — shoes with a firm heel counter, cushioned sole, slight heel-to-toe drop and good arch support. Avoid going barefoot on hard floors; wear supportive slippers or arch support sandals around the house.
- Arch supports and orthotic insoles — reduce strain on the plantar fascia and stabilise the heel. Clinical trials show good-quality prefabricated orthotics work about as well as custom-made ones for most people. Compare options for insoles for plantar fasciitis.
- Heel cups and heel pads — extra cushioning that is especially helpful for fat pad atrophy and bruised heels.
- Ice — 10–15 minutes after activity, or roll your foot over a frozen water bottle, to calm pain.
- Pain relief — paracetamol (acetaminophen) or anti-inflammatories such as ibuprofen, or anti-inflammatory gels, for short-term relief. Check with a pharmacist or doctor first, especially if you have stomach, kidney or heart problems.
- Weight management — even a modest weight loss reduces the load through your heels with every step.
Step 2: Supportive and clinician-led treatments
- Taping or strapping — low-dye taping supports the arch and gives short-term relief. How to tape your foot for plantar fasciitis.
- Night splints — hold the foot at 90° overnight so the plantar fascia and calf don’t tighten, reducing morning pain. Do night splints work?
- Compression socks and sleeves — may ease swelling and aching during long days on your feet. Do compression socks help?
- Physical therapy / physiotherapy — a structured stretching and strengthening program, manual therapy, soft tissue release and gait advice.
- Podiatry assessment — foot posture and gait analysis, footwear advice, padding, and custom orthotics where needed.
- Dry needling and acupuncture — some evidence for short-term pain relief as part of a wider program.
- Walking boot (CAM boot) — used for a few weeks for severe pain, stress fractures or a partial plantar fascia tear.
Step 3: Advanced treatments for stubborn heel pain
- Extracorporeal shockwave therapy (ESWT) — sound waves delivered to the heel to stimulate healing. Good evidence for chronic plantar fasciitis lasting longer than 3–6 months; usually 3–5 sessions.
- Corticosteroid injections — can give strong short-term relief (often weeks to a few months), but repeated injections carry a risk of fat pad atrophy and plantar fascia rupture, so they’re used sparingly. Also used for bursitis.
- Platelet-rich plasma (PRP) injections — concentrated platelets from your own blood injected into the fascia. Some studies suggest longer-lasting benefit than steroids; evidence is still developing.
- Botulinum toxin injections — an emerging option with mixed but encouraging evidence.
- Radiofrequency ablation and ultrasound-guided percutaneous procedures — minimally invasive options used in specialist clinics for chronic cases.
Read more in Beyond insoles: acupuncture, cortisone and shockwave therapy.
Step 4: Surgery
Surgery is considered only when significant pain persists after 6–12 months of well-followed non-surgical treatment.
- Gastrocnemius recession — lengthens a tight calf muscle to reduce pull on the heel; increasingly preferred because it leaves the plantar fascia intact.
- Plantar fascia release (fasciotomy) — partial release of the plantar fascia, open or endoscopic.
- Nerve decompression — for Baxter’s nerve entrapment or tarsal tunnel syndrome.
- Haglund’s / Achilles surgery — removing a bony prominence and inflamed bursa, sometimes with tendon repair, for chronic back-of-heel pain.
When is surgery necessary for plantar fasciitis?
Treatment by condition
| Condition | Treatments that usually help most |
|---|---|
| Plantar fasciitis / heel spur | Stretching and heel-raise strengthening, supportive shoes, arch support, night splints; ESWT for chronic cases |
| Fat pad atrophy | Cushioned heel cups, soft-soled shoes, avoiding barefoot walking; avoid steroid injections |
| Retrocalcaneal bursitis / Haglund’s | Open-backed or soft-backed shoes, heel lift, ice, anti-inflammatories; occasionally an injection |
| Insertional Achilles tendinopathy | Heel lift, progressive calf loading (no dropping below step level), ESWT |
| Baxter’s nerve / tarsal tunnel | Arch support, footwear changes, physiotherapy; injection or decompression surgery if persistent |
| Calcaneal stress fracture | Offloading in a walking boot for 4–8 weeks, then gradual return |
| Sever’s disease | Activity modification, calf stretches, heel cushioning; resolves with growth |
Exercises for plantar fasciitis and heel pain
Stretching and strengthening exercises can be useful to improve lower limb biomechanics, thereby reducing the stress put on the plantar fascia ligament. Please click here to see these exercises.
Supportive orthotics are one conservative treatment option for plantar fasciitis. The Footlogics orthotics for plantar fasciitis combine anatomical arch support and heel cushioning to help manage discomfort associated with this condition.
Frequently asked questions about plantar fasciitis and heel pain
1. What is the main cause of plantar fasciitis?
Plantar fasciitis is caused by repeated strain on the plantar fascia that is greater than the tissue can recover from. The most common triggers are a sudden increase in walking, running or standing, tight calf muscles, higher body weight, flat feet or high arches, and unsupportive or worn-out shoes. Usually several of these combine rather than one single cause.
2. What’s the difference between plantar fasciitis and a heel spur?
Plantar fasciitis is damage to the soft tissue band under the foot; a heel spur is a small bony growth on the heel bone where that band attaches. Spurs develop slowly from long-term pulling and are common in people with plantar fasciitis, but many people have spurs with no pain at all. In most cases the pain comes from the irritated tissue, not the spur, so both are treated the same way.
3. Is heel bursitis the same as plantar fasciitis?
No. Bursitis is inflammation of a small fluid-filled sac, most often at the back of the heel behind the Achilles tendon. It causes swelling and pain at the back of the heel, especially in stiff-backed shoes. Plantar fasciitis causes pain under the heel, typically worst on the first steps in the morning. The two need different treatment, so it’s worth getting the diagnosis right.
4. Can plantar fasciitis go away on its own?
Yes, plantar fasciitis often settles on its own, but it can take 6–18 months without treatment. Consistent stretching and strengthening, supportive footwear and reducing aggravating activity usually shorten recovery considerably. Ignoring it and pushing through the pain can turn it into a chronic problem.
5. What is the fastest way to relieve heel pain?
For quick relief, reduce time on your feet, ice the heel or roll it over a frozen bottle, take a short course of over-the-counter pain relief if suitable, and wear supportive shoes rather than going barefoot. Stretching your foot before getting out of bed reduces first-step pain. Taping the arch can give same-day relief while longer-term treatments take effect.
6. Should I keep walking with plantar fasciitis?
Yes, but within your limits. Gentle walking in supportive shoes keeps the tissue healthy, while long walks, hard surfaces and running can delay healing. A useful rule: if your pain is worse the next morning, you did too much the day before. Swap in cycling or swimming to stay fit while the heel settles.
7. Is heat or ice better for heel pain?
Ice is generally better after activity or when the heel is sore and throbbing, because it reduces pain. Gentle warmth before stretching can help a stiff calf and foot relax. Avoid applying ice directly to the skin or for more than 15 minutes, and skip both if you have reduced sensation or poor circulation in your feet.
8. Does losing weight help plantar fasciitis?
Yes. A higher body weight is one of the strongest risk factors for plantar fasciitis because it increases the load through the heel with every step. Even a modest weight loss can reduce heel pain and lower the chance of it coming back. Low-impact exercise such as cycling or swimming helps without aggravating the heel.
9. Can you get plantar fasciitis in both feet?
Yes, roughly 20–30% of people with plantar fasciitis have it in both feet. Heel pain in both feet that starts without any change in activity can sometimes point to an inflammatory condition such as ankylosing spondylitis, so it’s worth mentioning to your doctor.
10. Who should I see for heel pain?
A podiatrist or physical therapist is usually the best first point of contact for heel pain. A GP or family doctor can help with pain relief, blood tests and referrals. If pain persists after several months, you may be referred to a sports medicine physician or foot and ankle surgeon for advanced treatments.
11. Do cortisone injections work for heel pain?
Cortisone injections can give strong short-term relief from plantar fasciitis and bursitis, often for several weeks to a few months. They don’t fix the underlying cause, and repeated injections can thin the heel fat pad or weaken the plantar fascia. Most clinicians limit their use and combine them with stretching, strengthening and footwear changes.
12. Is shockwave therapy effective for plantar fasciitis?
Shockwave therapy (ESWT) has good evidence for chronic plantar fasciitis that hasn’t improved after 3–6 months of standard treatment. It usually involves 3–5 short sessions about a week apart and is non-invasive. It’s less useful for recent heel pain, which tends to respond to simpler treatments.
13. Can heel pain be a sign of something serious?
Rarely. Most heel pain is mechanical and improves with self-care. See a doctor promptly if you have severe pain after an injury, can’t bear weight, notice swelling with redness or fever, have spreading numbness or tingling, or have diabetes and any heel pain or skin change.
14. Can children get plantar fasciitis?
Plantar fasciitis is uncommon in children. Heel pain in active children aged about 8–14 is far more likely to be Sever’s disease, an irritation of the heel growth plate during growth spurts. It usually settles with reduced activity, calf stretches and heel cushioning, and goes away once growth is complete.
Looking for arch support for heel pain? Podiatrist-designed orthotics for different arch types, shoes and sports. Find the right insole for plantar fasciitis →
References
- Trojian T, Tucker AK. Plantar Fasciitis. American Family Physician. 2019;99(12):744–750. — lifetime incidence about 10%; around 1 million US doctor visits a year; about 80% improve with treatment.
- Rathleff MS, Mølgaard CM, Fredberg U, et al. High-load strength training improves outcome in patients with plantar fasciitis: a randomized controlled trial with 12-month follow-up. Scand J Med Sci Sports. 2015;25(3):e292–e300. — heel raises with a towel under the toes reduced pain and improved function faster than stretching at 3 months.
- Buchanan BK, Sina RE, Kushner D. Plantar Fasciitis. StatPearls. 2024. — degenerative rather than inflammatory condition; overview of causes and treatment.
- Whittaker GA, Munteanu SE, Menz HB, et al. Foot orthoses for plantar heel pain: a systematic review and meta-analysis. Br J Sports Med. 2018;52:322–328. — the single orthotic reference retained on this page.
SHOP BY FOOT COMPLAINT
common aches & pains
Learn more about different foot conditions and how Footlogics orthotics can help..